
Quick answer
Alpha blockers can relieve BPH urinary symptoms by relaxing smooth muscle around the prostate and bladder outlet, but the individual drugs differ enough in blood-pressure effects, food instructions, renal considerations and ejaculation effects that “take an alpha blocker” is not a complete decision.
What this page helps you decide
- The class effect is simple; the choice is not
- Blood pressure separates the older systemic agents
- Ejaculation can be the deciding trade-off
Evidence used on this page: DailyMed: Tamsulosin labeling search · NIDDK: Enlarged Prostate (BPH)
The class effect is simple; the choice is not
Tamsulosin, alfuzosin, silodosin, doxazosin and terazosin all reduce alpha-1–mediated smooth-muscle tone. That can improve a weak stream, hesitancy and incomplete-emptying sensations without waiting for prostate tissue to shrink. The shared mechanism explains why they can work relatively quickly. It does not mean their practical profiles are identical.
Blood pressure separates the older systemic agents
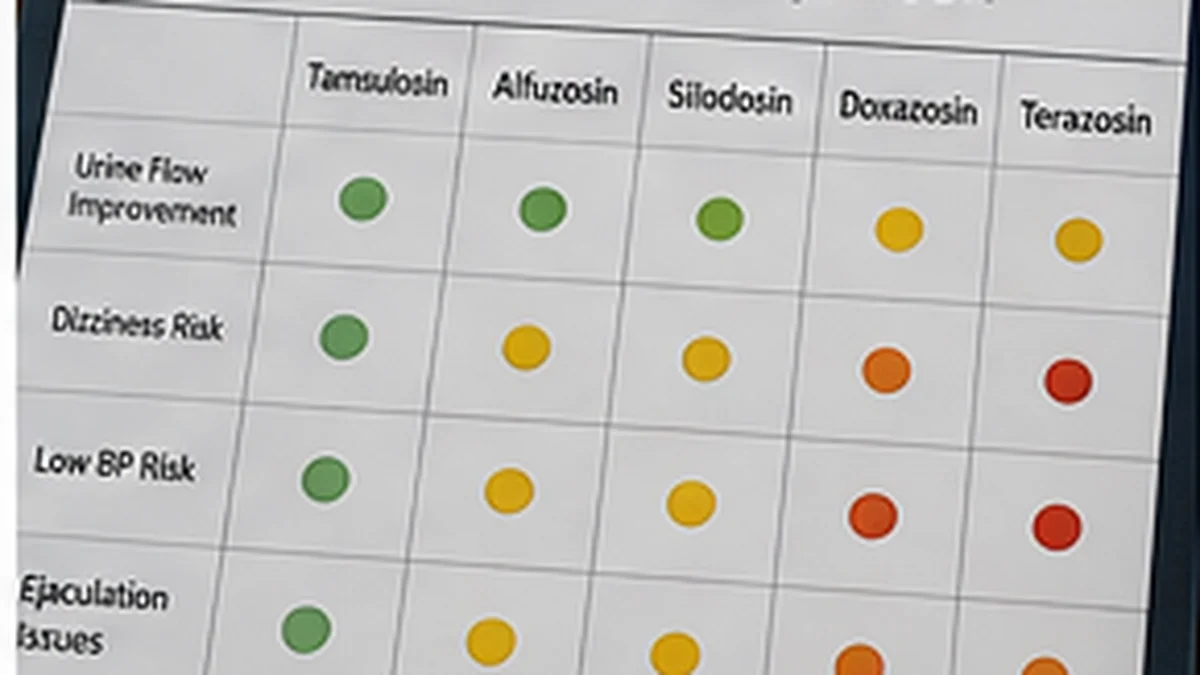
Doxazosin and terazosin are also antihypertensive medicines. Their initiation and titration are built around orthostatic hypotension and first-dose effects, so blood pressure and fall risk belong at the center of the discussion. Tamsulosin, alfuzosin and silodosin can still cause dizziness or low blood pressure, but they are not used as interchangeable blood-pressure drugs.
Ejaculation can be the deciding trade-off
Silodosin and tamsulosin deserve particular attention when ejaculation preservation matters. Reduced or retrograde ejaculation can be more important to an individual patient than a small average difference in urinary symptom improvement. A treatment comparison that ignores this preference can recommend the “right” drug for the wrong person.
Food, kidney and liver details change real-world use
Alfuzosin extended release is taken immediately after the same meal. Silodosin is taken with a meal and has renal-dose considerations. Alfuzosin has hepatic and QT-related labeling cautions. These details are not clerical trivia; inconsistent use or an overlooked organ-function issue can change both exposure and tolerability.
Alpha blockers do not shrink an enlarged prostate
Symptom relief from an alpha blocker does not prove the gland is smaller or that progression risk has changed. Men with a substantially enlarged prostate may still need a discussion about finasteride, dutasteride or a procedure, especially when retention, recurrent infection, stones, bleeding or kidney effects enter the picture.
Switching within the class should solve a specific problem
A switch can make sense because of dizziness, ejaculation effects, food requirements, renal function or hypertension goals. Repeatedly cycling through alpha blockers without defining the unresolved symptom can instead delay evaluation of bladder overactivity, nocturnal urine production, urethral disease or fixed obstruction.
| Medicine | Practical distinction |
|---|---|
| Tamsulosin | Same-meal routine; ejaculation and orthostatic effects |
| Alfuzosin | Extended release after same meal; hepatic/QT cautions |
| Silodosin | Prominent ejaculation changes; renal dosing |
| Doxazosin | Also treats hypertension; gradual titration |
| Terazosin | Bedtime first dose; first-dose syncope concern |
Frequently asked questions
Do alpha blockers shrink the prostate?
No. Their main BPH action is smooth-muscle relaxation, not tissue reduction.
Which alpha blocker has the least blood-pressure effect?
There is no universal answer; selectivity, baseline blood pressure, other drugs and individual response matter.
Which alpha blockers are also hypertension drugs?
Doxazosin and terazosin are used for hypertension as well as BPH.
Which alpha blockers affect ejaculation most?
Silodosin and tamsulosin are particularly associated with ejaculation changes.
Does alfuzosin have to be taken with food?
The extended-release label directs dosing immediately after the same meal each day.
Does silodosin require kidney-dose adjustment?
Yes, renal function is an important part of silodosin dosing and severe renal impairment is a contraindication.
Can alpha blockers cause fainting?
Orthostatic hypotension and syncope can occur, especially with systemic agents and during initiation or titration.
Do alpha blockers change PSA?
They do not create the predictable PSA suppression seen with finasteride or dutasteride.
How fast do alpha blockers work?
They are generally judged over days to weeks rather than the months required for prostate-shrinking therapy.
Can two alpha blockers be taken together?
Using two drugs from the same class is not a routine BPH strategy and should not be attempted without specialist guidance.
What if an alpha blocker helps flow but not nocturia?
Nocturia can come from nighttime urine production, sleep disorders or bladder storage problems that alpha blockade does not address.
When should a procedure be discussed?
Persistent severe symptoms, complications, unacceptable side effects or fixed obstruction can shift the decision toward a procedure.
Evidence used on this page
Major treatment claims are anchored to the sources cited on this page, prioritizing official drug labeling, government health agencies, regulators, and professional guidelines.
- Official drug labeling
- Government health source
Sources
How to use the Alpha Blockers hub
This page is designed as a decision hub rather than a list of keywords. The useful question is not simply “what is alpha blockers?” but which treatment question the reader is actually trying to resolve. Start with the symptom pattern, then move to mechanism, expected time horizon, side effects, alternatives and procedure thresholds. That sequence prevents a common research mistake: comparing treatments that solve different problems as though they were interchangeable.
The Alpha Blockers section groups pages by decision intent. The alpha-blocker hub focuses on differences in selectivity, blood-pressure effects, ejaculation effects and practical treatment fit. A reader with bothersome symptoms but no treatment history needs a different path from someone already taking medication, dealing with a side effect, or considering a procedure after an incomplete response.
What makes a treatment decision genuinely different
Distinct BPH decisions differ by more than a drug or procedure name. Important dimensions include whether the goal is faster symptom relief or longer-term prostate reduction, whether erectile or ejaculatory function matters to the decision, whether blood pressure limits an option, whether PSA interpretation is affected, and whether symptoms suggest fixed obstruction rather than a medication problem.
That is why this site separates comparison, side-effect, medication-failure and procedure content. Those are different decision stages. Combining them into one giant article would be tidy for a spreadsheet and miserable for a person trying to answer one concrete question.
When online research should stop and clinical reassessment should start
Educational comparison has limits. Acute urinary retention, fever with urinary symptoms, visible blood in the urine, fainting, severe pain or rapidly worsening symptoms need prompt medical assessment. Persistent symptoms despite treatment also deserve review because bladder dysfunction, infection, urethral narrowing, sleep-related causes of nocturia and other conditions can overlap with BPH symptoms.
The practical purpose of this hub is to help organize better questions for a clinician, not to encourage unsupervised dose changes or medication switching.
A simple decision framework
First define the dominant problem: weak stream, urgency, frequency, nocturia, side effects, slow response, loss of response, sexual-function concerns or fear of progression. Second identify what the current treatment is designed to change. Third compare the next options using the same criteria rather than switching criteria halfway through the comparison. Finally, decide what information is missing before the next appointment.
A useful treatment page should leave the reader with a narrower question and a clearer next step. If a page merely repeats that “results vary” for twelve paragraphs, it has technically used words but has not delivered much intelligence.