Lecturas útiles a continuación: Compare BPH Medications · Silodosin (Rapaflo) for BPH
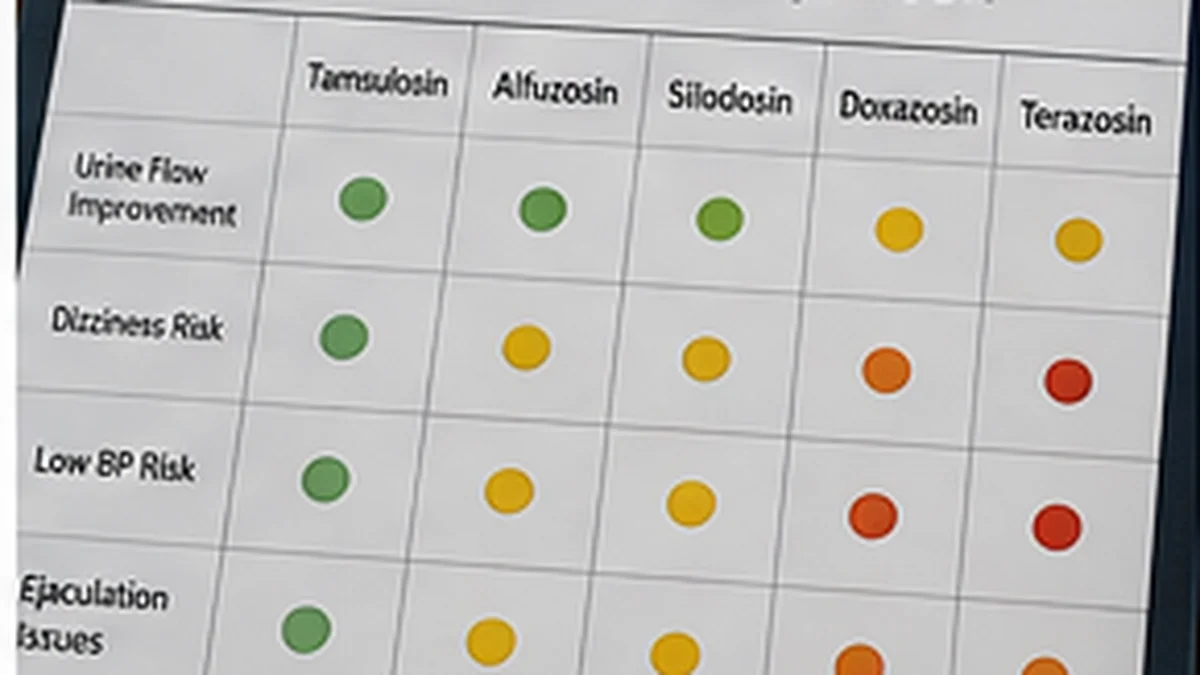
Silodosin vs Terazosin: what are you actually comparing?
Silodosin is a relatively uroselective alpha blocker for BPH. U.S. labeling highlights retrograde ejaculation among common adverse reactions and also warns about postural hypotension.
Terazosin is used for symptomatic BPH and hypertension. U.S. labeling emphasizes marked blood-pressure lowering, postural hypotension and syncope around treatment initiation and dose changes.
Searches for “Rapaflo vs Hytrin” usually reflect a treatment-selection problem rather than curiosity about pharmacology. The useful comparison is not whether both can improve lower urinary tract symptoms. They can. The useful comparison is which adverse-event profile, dosing context and comorbidity fit better with the person in front of the prescriber.
Direct comparison
| Decision factor | Silodosin (Rapaflo) | Terazosin (Hytrin) |
|---|---|---|
| Class | Alpha blocker | Alpha blocker |
| Primary BPH role | Symptom relief through smooth-muscle relaxation | Symptom relief through smooth-muscle relaxation |
| Blood-pressure consideration | Postural hypotension can occur, especially when treatment begins. | First-dose and dose-escalation hypotension, dizziness and syncope are major labeled considerations. |
| Sexual/ejaculation consideration | Retrograde ejaculation is a prominent labeled adverse reaction. | Sexual side effects may be discussed, but orthostatic effects are often a more prominent selection issue. |
| Prostate shrinkage | No | No |
| PSA-lowering effect | Not a defining class effect | Not a defining class effect |
Why “same class” does not mean “same choice”
The AUA guideline does not rank one alpha blocker as universally superior. Instead, it tells clinicians to choose among the class based on age, comorbidities and different adverse-event profiles, specifically naming ejaculatory dysfunction and changes in blood pressure. That is the correct frame for this comparison.
If the person already has low blood pressure, takes several antihypertensives, has a history of falls, places a high priority on preserving ejaculation, or has planned cataract surgery, those details can matter more than small average differences in symptom scores. Conversely, if urinary symptoms remain poorly controlled, the more important question may be whether the problem is still suited to alpha-blocker monotherapy at all.
What neither drug is designed to do
Neither Silodosin nor Terazosin is a 5-alpha-reductase inhibitor. They are not prescribed to shrink prostate tissue through DHT suppression, and they do not substitute for finasteride or dutasteride when prostate-volume reduction or long-term progression risk is a central treatment goal. That distinction is easy to lose when all BPH medicines are treated as if they perform the same job.
They also do not eliminate the need to reassess persistent symptoms. Weak stream, urgency, nocturia and incomplete emptying can reflect more than prostate smooth-muscle tone. A clinician may need to consider prostate size, bladder function, residual urine, infection, medications, neurologic conditions or a procedure pathway.
How to use this information in a treatment decision
BPH treatment is not a contest to find a universally “best” alpha blocker. The American Urological Association lists alfuzosin, doxazosin, silodosin, tamsulosin and terazosin as treatment options for bothersome moderate-to-severe LUTS/BPH, and specifically says selection should take age, comorbidities and differing adverse-event profiles into account. That matters because the drugs share a class but not identical practical trade-offs.
For a useful clinician discussion, bring a short symptom record covering nighttime urination, urgency, weak stream, hesitancy, incomplete emptying, dizziness, falls, blood-pressure readings if relevant, and any sexual or ejaculation changes. Also bring a complete medication list. Alpha blockers can interact with the rest of a treatment plan, and blood-pressure-lowering effects are especially important when antihypertensives, nitrates or PDE5 inhibitors are involved.
Separate short-term symptom relief from long-term progression questions. Alpha blockers improve symptoms by relaxing smooth muscle; they do not shrink the prostate in the same way as finasteride or dutasteride. If prostate enlargement, PSA, progression risk, persistent symptoms or complications are central to the case, the right comparison may extend beyond the alpha-blocker class.
Questions to discuss with your clinician
- Which treatment goal matters most in my case: urinary symptom relief, blood-pressure management, fewer ejaculation effects, or another priority?
- How do my age, fall risk, cardiovascular history and other medicines affect alpha-blocker choice?
- What should I expect during the first days or weeks, and when should response be reassessed?
- Which dizziness, fainting, urinary or sexual symptoms should prompt an earlier call?
- If this alpha blocker is not a good fit, should we compare another alpha blocker, another medication class, combination treatment or a procedure?
Preguntas frecuentes
Do alpha blockers shrink the prostate?
No. Alpha blockers primarily relax smooth muscle to improve urinary symptoms. Drugs such as finasteride and dutasteride work differently and can reduce prostate volume over time.
Do alpha blockers affect PSA the way finasteride does?
Alpha blockers are not generally used to reduce PSA. PSA interpretation is a different issue with 5-alpha-reductase inhibitors such as finasteride and dutasteride.
Can alpha blockers cause dizziness?
Yes. Dizziness and postural blood-pressure effects are recognized class concerns, although the degree and individual risk differ among drugs.
Why does blood pressure matter when choosing an alpha blocker?
Some alpha blockers have more systemic vascular effects. Age, baseline blood pressure, antihypertensive medicines, fall risk and other drugs can change the practical risk.
Can alpha blockers affect ejaculation?
Yes. Ejaculatory dysfunction is an important treatment-selection issue, particularly with some more uroselective agents. The exact profile differs by drug.
Can two alpha blockers be taken together?
Combining alpha blockers is generally not a routine BPH strategy and can increase adverse effects. Silodosin labeling specifically says it should not be used with other alpha blockers.
What should I tell my eye surgeon?
Tell an ophthalmologist about current or previous alpha-blocker use before cataract surgery because the class is associated with intraoperative floppy iris syndrome.
Can an online page tell me which alpha blocker to use?
No. It can clarify trade-offs and questions, but medication selection requires clinical evaluation of symptoms, blood pressure, other medicines and health history.
What if an alpha blocker is not working?
Persistent symptoms deserve reassessment rather than an automatic dose change. The clinician may review diagnosis, adherence, prostate size, bladder function, another drug class, combination therapy or procedures.
Should I stop an alpha blocker if I feel dizzy?
Do not stop or restart prescription medication solely from an online article. Contact the prescriber, particularly if dizziness is new, severe, recurrent or associated with fainting.
Are alpha blockers used only for BPH?
Some alpha blockers, including doxazosin and terazosin, are also used for hypertension. That dual role is one reason blood-pressure context matters.
When do urinary symptoms need urgent medical care?
Seek urgent evaluation for inability to urinate, severe lower abdominal pain, fever with urinary symptoms, visible blood in urine, fainting or other severe symptoms.
Fuentes
Source selection focuses on decision-relevant prescribing and guideline information so readers can distinguish class-wide considerations from medication-specific warnings.
Zenn7 prioritizes U.S. prescribing information, public-health references and clinical guidelines. Links open in a new tab.