Quick answer
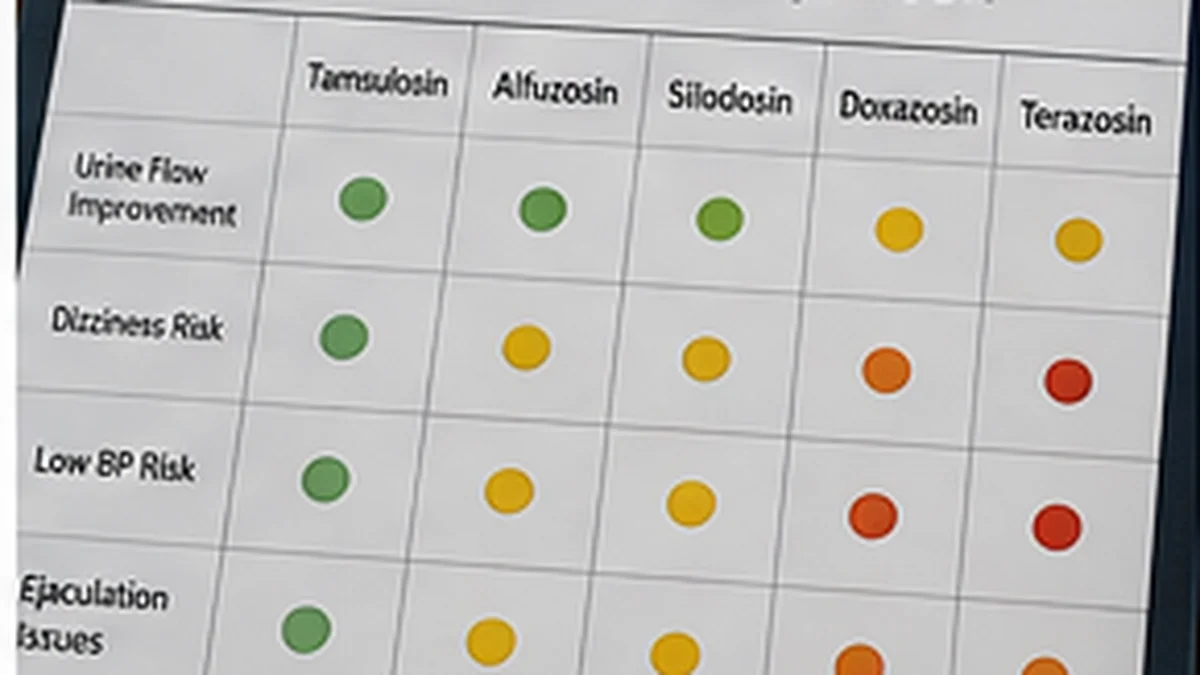
Tamsulosin and Silodosin can both appear in BPH therapeutic approach plans, but they are not interchangeable. Both are urinary-focused alpha blockers, but their selectivity and adverse-effect patterns can make the choice feel very different. The better fit depends on ejaculatory function, dizziness, blood-pressure tolerance, symptom urgency and previous alpha-blocker tolerance.
What this page helps you decide
- Alpha-blocker selectivity and ejaculation trade-offs
- Side-by-side prescribing judgment table
- Why Tamsulosin versus Silodosin is a distinct decision
Evidence used on this page: NIDDK: Enlarged Prostate (BPH) · DailyMed drug labeling · American Urological Association: BPH guidance
Useful next reads: Tamsulosin guide · Silodosin guide · Compare BPH medications
Alpha-blocker selectivity and ejaculation trade-offs
Tamsulosin is a selective alpha-1 blocker that relaxes smooth muscle around the prostate and bladder outlet. Silodosin is a highly selective alpha-1A blocker that targets prostate and bladder-neck smooth muscle. Because both are used primarily to reduce the dynamic resistance created by smooth muscle around the outlet, prostate shrinkage is not the purpose of either drug.
The meaningful comparison therefore sits in tolerability and context. With Tamsulosin, can cause dizziness or postural blood-pressure urinary difficulties; with Silodosin, may have a different balance of urinary selectivity and blood-pressure effects. sexual tolerability issues also deserve separate discussion: ejaculatory changes can matter for some men, whereas ejaculatory dysfunction is an especially prescribing judgment-relevant counseling point.
That means a previous episode of standing dizziness, a history of falls, use of antihypertensive medicines, and the importance of ejaculation or sexual function can be more useful prescribing judgment variables than simply asking which alpha blocker is “stronger.”
Side-by-side prescribing judgment table
| prescribing judgment factor | Tamsulosin | Silodosin |
|---|---|---|
| Drug class | Selective Alpha-1 Blocker | Highly Selective Alpha-1A Blocker |
| Primary therapeutic approach aim | Relaxes smooth muscle around the prostate and bladder outlet | Targets prostate and bladder-neck smooth muscle |
| degree of prostate enlargement | Does not shrink the prostate | Does not shrink the prostate |
| Practical timing | Often used when relatively prompt symptom relief is the main treatment objective | Is used for symptom relief rather than structural prostate reduction |
| Blood-pressure context | Can cause dizziness or postural blood-pressure urinary difficulties | May have a different balance of urinary selectivity and blood-pressure effects |
| Sexual-function discussion | Ejaculatory changes can matter for some men | Ejaculatory dysfunction is an especially prescribing judgment-relevant counseling point |
| PSA context | Does not have the psa-lowering effect associated with 5-alpha-reductase inhibitors | Does not create the psa interpretation issue seen with finasteride or dutasteride |
This comparison is educational. Individual suitability depends on medical history, prostate characteristics, blood-pressure tolerance, other medicines, therapeutic approach goals and prescribing professional judgment.
Why Tamsulosin versus Silodosin is a distinct decision
Tamsulosin and Silodosin should not be compared as though they are interchangeable names on the same prescription shelf. Tamsulosin is best understood as a uroselective alpha blocker, while Silodosin is a highly alpha-1A selective blocker. That difference changes what “success” means, how quickly a response is judged, which adverse effects deserve attention, and what information should be reviewed before switching.
The most useful comparison lens for Tamsulosin is fast urinary symptom relief and ejaculation trade-off. For Silodosin, the central lens is maximum urinary selectivity versus ejaculation burden. A patient whose main priority is rapid relief, blood-pressure stability, ejaculation preservation, erectile function, prostate shrinkage or PSA interpretation can therefore reach a different conclusion even when both treatments are reasonable options.
| Decision factor | Tamsulosin | Silodosin |
|---|---|---|
| Treatment identity | uroselective alpha blocker | highly alpha-1A selective blocker |
| Blood-pressure lens | generally less systemic BP effect than older nonselective agents | low vascular emphasis is attractive when orthostasis matters |
| Sexual-function lens | ejaculation changes are a key counseling point | ejaculatory dysfunction is especially important to discuss |
| Dosing/timing issue | usually fixed-dose rather than BP titration | renal function can affect dosing |
| Best framing | fast urinary symptom relief and ejaculation trade-off | maximum urinary selectivity versus ejaculation burden |
Patient scenarios where the Tamsulosin–Silodosin choice changes
If the dominant problem is weak stream with a need for relatively rapid symptom relief, the comparison should emphasize onset and tolerability rather than long-term structural effects. If the dominant concern is a large prostate or progression risk, the relevance of each mechanism changes. If sexual function is the reason for reconsidering treatment, the conversation should separate erectile function from ejaculation because those are not the same outcome.
Blood pressure also changes the decision. For Tamsulosin, generally less systemic BP effect than older nonselective agents. For Silodosin, low vascular emphasis is attractive when orthostasis matters. That matters more in someone with antihypertensive therapy, orthostatic symptoms, falls risk or cardiovascular constraints than it does in a patient without those issues.
Dosing details can also decide the practical winner. With Tamsulosin, usually fixed-dose rather than BP titration. With Silodosin, renal function can affect dosing. Adherence and administration details are not glamorous, but neither is publishing a comparison that ignores the reason a drug fails in real life.
Questions that are specific to choosing between Tamsulosin and Silodosin
- Which of my symptoms is Tamsulosin most likely to improve, and which is Silodosin most likely to improve?
- How soon should I expect a meaningful response from each option before we judge it?
- Which adverse effect is most likely to make me stop Tamsulosin, and which is most likely with Silodosin?
- Does my blood pressure, fall risk or cardiovascular medication list favor one option?
- Do prostate size, PSA interpretation or risk of progression change the value of either drug?
- If the first choice is inadequate, would switching, combining therapy or discussing a procedure make more sense?
Frequently asked questions about Tamsulosin versus Silodosin
What is the biggest practical difference between Tamsulosin and Silodosin?
Tamsulosin is a uroselective alpha blocker, whereas Silodosin is a highly alpha-1A selective blocker. That difference changes the expected response timeline, monitoring priorities and the reasons a clinician might prefer one over the other.
Which works faster for urinary symptoms, Tamsulosin or Silodosin?
For Tamsulosin, the response window often judged over days to a few weeks for symptom relief. For Silodosin, it usually assessed relatively quickly for urinary symptom relief. The comparison should use an appropriate timeline for each mechanism rather than declaring one a failure too early.
How do Tamsulosin and Silodosin differ on blood-pressure risk?
With Tamsulosin, can still cause dizziness or orthostatic symptoms, but blood-pressure treatment is not its purpose. With Silodosin, has less vascular emphasis than older nonselective alpha blockers, though dizziness can still occur. Baseline blood pressure, antihypertensive medicines, dizziness and fall history can therefore change which option is easier to tolerate.
Which has the more important sexual-function trade-off?
For Tamsulosin, ejaculatory changes are a prominent counseling issue. For Silodosin, ejaculatory dysfunction is a major distinguishing adverse effect. Erectile function, libido and ejaculation should be discussed separately because one treatment can affect these domains differently.
Does Tamsulosin or Silodosin shrink an enlarged prostate?
Tamsulosin: does not shrink the prostate. Silodosin: does not shrink the prostate. This matters when prostate volume or long-term progression risk is central to the treatment goal.
How do Tamsulosin and Silodosin affect PSA interpretation?
Tamsulosin: does not materially suppress PSA. Silodosin: does not materially suppress PSA. If either treatment changes PSA biology, the clinician should interpret serial values in that treatment context.
Which patient priority most strongly favors Tamsulosin?
The strongest reason to focus on Tamsulosin is usually administration consistency and ejaculation priorities. That priority should still be weighed against symptom pattern, prostate anatomy, other medicines and adverse-effect tolerance.
Which patient priority most strongly favors Silodosin?
The strongest reason to focus on Silodosin is usually renal dosing and ejaculation burden. It becomes more relevant when that issue matters more than the advantages offered by Tamsulosin.
Can a clinician switch directly from Tamsulosin to Silodosin?
Switching depends on why Tamsulosin is being stopped, how Silodosin works, interaction risk and whether a washout or overlap is appropriate. The prescriber should give the specific transition plan rather than the patient improvising one.
Could Tamsulosin and Silodosin ever be used together?
Combination therapy makes sense only when the mechanisms and safety profile complement each other. Some BPH drug classes are intentionally combined, while pairing two treatments with overlapping effects may add risk without enough benefit.
What if neither Tamsulosin nor Silodosin controls the main symptom?
Persistent symptoms should trigger a reassessment of the symptom driver, adherence, treatment duration and anatomy. Urgency, nocturia and weak flow do not always share the same cause, and medication comparisons cannot rule out bladder, sleep, infection or obstruction-related contributors.
When should the Tamsulosin versus Silodosin decision become a procedure discussion?
A procedure discussion becomes more relevant when bothersome symptoms persist despite an adequate medical strategy, adverse effects make medication difficult to continue, or objective findings suggest that medication alone is unlikely to meet the treatment goal.
Evidence used on this page
Major treatment claims are anchored to the sources cited on this page, prioritizing official drug labeling, government health agencies, regulators, and professional guidelines.
- Government health source
- Official drug labeling
- Professional guideline
Sources
Sources are provided for general medical context. Drug labeling and professional guidance can change; clinicians should use current prescribing information and guidelines.
Related therapeutic approach decisions
Medical note: This page is educational and does not diagnose BPH or tell you to start, stop, or change a prescription. Seek prompt care for urinary retention, fever with urinary urinary difficulties, severe pain, or substantial blood in the urine.